What Is the Anion Gap?
The anion gap is a computed figure derived from common electrolytes in a serum chemistry panel. It helps clinicians gauge acid-base balance and detect types of acid-base disorders, especially when reviewing possible metabolic acidosis. Although it is not a directly measured value, it reflects the difference between major positively charged and negatively charged particles in blood chemistry.
In practical terms, the anion gap helps estimate the balance between unmeasured anions and unmeasured cations. A change in this balance can signal an underlying electrolyte imbalance, a metabolic derangement, or a specific disease process that needs further medical evaluation. Because it uses routine serum electrolytes, it is a useful diagnostic tool in everyday care.
The anion gap is often interpreted alongside the basic metabolic panel and sometimes with blood gas analysis to understand a patient’s acid-base status. It is best thought of as a laboratory assessment that guides clinical judgment rather than replacing it. In that sense, it serves as a risk indicator for certain conditions and a guide to next steps in the diagnostic evaluation.
Anion Gap Calculation Formula
The usual anion gap calculation formula is written as:
Anion gap = sodium - (chloride + bicarbonate)
In this calculation, sodium is the major measured cation, while chloride and bicarbonate are the major measured anions. The difference estimates the amount of anion concentration not directly measured in routine testing.
Different laboratories may use different calculation methods. Certain labs include potassium, though common clinical formulas do not. Because the details can vary, the reference interval or reference range may also differ depending on the laboratory and the assay used.
The formula is straightforward, but the clinical interpretation is more complex. A elevated value can point toward high anion gap metabolic acidosis, while a below-normal value may suggest a measurement issue, protein abnormality, or a shift in electrolyte balance. This is why the formula is only the starting point for clinical interpretation.
In what way the Anion Gap Calculator Works
An Anion Gap Calculator automates the formula and allows users to quickly enter input values for sodium, chloride, and bicarbonate. Once the measured electrolytes are entered, the calculator performs the calculation and displays the calculation result.
Many calculator tools are created to minimize manual errors and streamline the review of test results. This approach makes them especially useful during a busy medical evaluation, when quick pattern recognition is important. The calculator can also provide a more structured interpretation guide for clinicians and students training how to identify abnormal patterns.
A good calculator does more than simply return a number. It can help users evaluate the result with a reference range, assess whether serum albumin may be affecting the result, and evaluate the possibility of a corrected value. In that way, the calculator becomes part of a broader laboratory assessment and not just a math tool.
As an example, if the sodium level is 140, chloride is 102, and bicarbonate is 24, the formula would give an anion gap of 14. Whether that is normal depends on the lab’s reference range and the clinical context. This shows why the Anion Gap Calculator should be used with the patient’s full picture in mind.
Typical Anion Gap Range
The normal anion gap is not the same across all laboratories because different methods and measurement systems affect the normal range. In many settings, the interval is based on the lab’s own laboratory values and assay characteristics. For that reason, the most accurate comparison is always to the specific reporting lab’s listed range.
Albumin plays a major role in shaping the observed gap because it is an important unmeasured anion. If serum albumin is low, the apparent gap may also be lower than expected even when other processes are present. This is why a single number should not be interpreted in isolation.
Understanding the normal range is essential for identifying whether a result reflects a true physiologic change or simply normal variation. The goal is not to memorize one universal cutoff, but to interpret the result against the proper reference range and the patient’s overall condition.
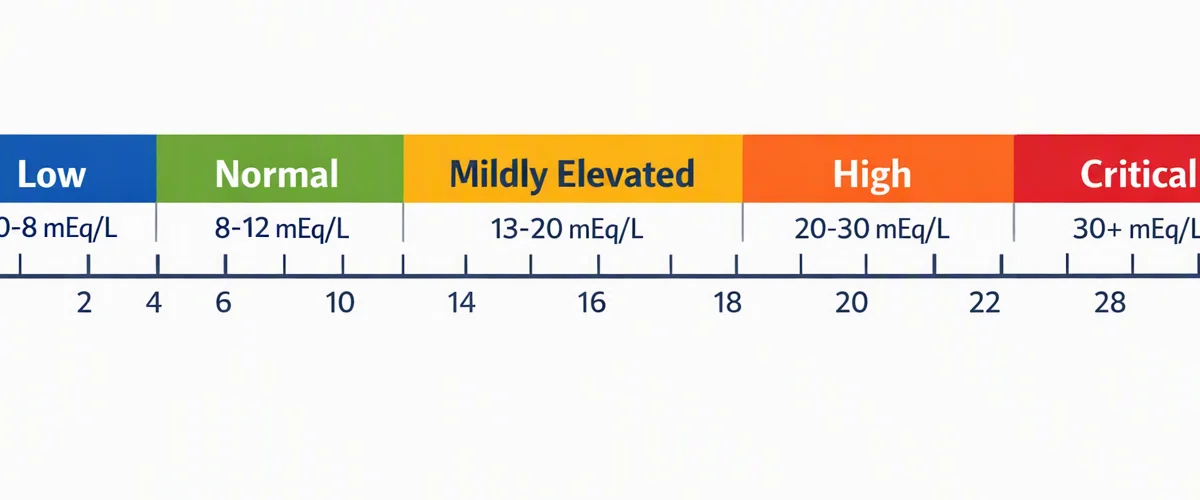
When reviewing anion gap values, clinicians look for consistency across the patient’s electrolyte profile, symptoms, and other labs. The number becomes more meaningful when paired with acid-base status, serum chemistry trends, and the broader clinical picture.
High Anion Gap Reasons
An elevated anion gap often points to the presence of additional acids in the body and is a key clue in high anion gap metabolic acidosis. This pattern reflects the accumulation of unmeasured acids that consume bicarbonate while leaving the gap widened. In many cases, this is one of the most helpful ways to narrow the differential diagnosis of metabolic acidosis.
Common causes are lactic acidosis, ketoacidosis, and uremia. Lactic acidosis may develop when tissues are underperfused or under oxygen stress. Ketoacidosis commonly occurs with insulin deficiency or prolonged starvation states. Uremia indicates reduced kidney function and the buildup of acid-related waste products.
Additional contributors can include toxic ingestions and severe metabolic disruption, but the core idea remains the same: the gap rises because there are more unmeasured anions than expected. This keeps the anion gap a valuable diagnostic tool for identifying a specific type of acid-base disorder.
When the result is high, clinicians often combine it with blood gas analysis and the basic metabolic panel to confirm the pattern and determine severity. A high result alone is not a diagnosis; it acts as a signpost that directs the diagnostic evaluation toward the likely cause.
Decreased Anion Gap Causes
A low anion gap is less common than a high one, but it can still be important clinically. One of the most frequent explanations is hypoalbuminemia, because reduced albumin decreases the contribution of unmeasured anions. Without enough albumin, the calculated difference may narrow even if other aspects of acid-base physiology remain abnormal.
Another major cause is multiple myeloma, where abnormal proteins can shift the balance of charged particles in the blood. In such cases, the low gap may be a clue to an underlying plasma cell disorder that requires further medical evaluation. Although not every low value points to a serious illness, it should not be ignored without proper interpretation.
Lab error is also a significant consideration. A specimen problem, instrument issue, or reporting mistake can produce an unexpectedly low result. Because of that, repeating the test and reviewing the underlying serum electrolytes is often recommended when the value does not fit the clinical picture.
Occasionally, shifts in electrolyte balance or changes in unmeasured cations can contribute. The key is to consider the low value as part of a broader assessment rather than a single finding.
Revised Anion Gap and Albumin Correction
The corrected anion gap adjusts the original result for the influence of serum albumin. This albumin adjustment matters because albumin is a significant contributor to the body’s net negative charge and substantially affects the computed gap. If albumin is low, the plain number can underestimate the true acid burden.
Using a corrected value enhances acid-base assessment, especially when evaluating complex cases of metabolic acidosis. It allows clinicians reduce the risk of missing an elevated gap that is masked by hypoalbuminemia. In other words, the corrected version often provides a clearer picture of the patient’s actual acid-base state.
The correction approach changes by method, but the principle is the same: adjust low AG diagnostic considerations the observed gap based on albumin concentration and then interpret the revised number against the appropriate expected range. This adds precision to the overall clinical reading and can affect how urgently a result is pursued.
Whenever albumin is significantly lowered, it is wise to interpret the anion gap cautiously. A seemingly normal uncorrected result may still mask a clinically important disorder, so the corrected anion gap can be a more reliable reflection of the patient’s true metabolic state.
Typical Pitfalls When Using the Equation
One recurring problem is measurement error. Minor errors in sodium, chloride, or bicarbonate can change the final value sufficiently to change interpretation. This is especially relevant when the result is close to the higher or lower edge of the reference range.
A further issue relates to electrolyte units. A calculator or user must be sure the values are entered in the same units specified by the formula and the lab report. Even simple formatting mistakes can lead to a misleading calculation result.
It is equally important not to overlook related analytes such as ionized calcium and magnesium. While they are not part of the basic formula, abnormal levels can affect the body's overall balance and shape the broader interpretation. These factors can influence how a clinician thinks about the patient’s blood chemistry.
In the end, users sometimes forget that the anion gap is a supportive measure, not a complete diagnosis. It should be considered alongside symptoms, the basic metabolic panel, and other findings. Overreliance on the number alone can lead to missed context and weaker clinical judgment.
When to Consider the Anion Gap in Medicine
The anion gap is most useful when evaluating metabolic acidosis, especially if the cause is not immediately obvious. It helps separate common patterns of acid-base disturbance and guides next steps in the diagnostic evaluation. In this setting, it functions as a practical marker of electrolyte imbalance and a possible clue to serious illness.
Clinicians often order or review it with a blood gas analysis to better understand acid-base status. The combination of blood gas findings, the basic metabolic panel, and the gap calculation provides a fuller picture than any single test. This makes the result more valuable in real-world medical evaluation.
It is additionally helpful when monitoring patterns over time. A varying gap may suggest improvement or worsening of an underlying metabolic derangement. In this way, it can serve as a valuable risk indicator and surveillance tool.
Because the result depends on multiple measured values, it can be particularly informative when the diagnosis is uncertain. It helps clinicians recognize whether the issue is likely a elevated-gap process, a decreased-gap pattern, or something affected by lab error or changed protein levels. That makes it a valuable component of routine laboratory assessment.
Frequently Asked Questions
What is the formula for calculating the anion gap?
The standard formula is sodium - (chloride + bicarbonate). It uses the measured electrolytes from a chemistry panel to calculate the difference between unmeasured anions and unmeasured cations.
What is a normal anion gap value?
The normal range depends on the laboratory’s reference range and measurement method. Because laboratory values can vary, the most accurate comparison is the range listed with the patient’s report.
What causes a high anion gap?
A high anion gap is commonly caused by high anion gap metabolic acidosis, including lactic acidosis, ketoacidosis, and uremia. These conditions raise unmeasured acids and increase the gap.
Why is albumin correction important in the anion gap?
Albumin correction matters because serum albumin is a major unmeasured anion. If albumin is low, the uncorrected result may mask a clinically important disorder, so the corrected anion gap gives better acid-base interpretation.
Can a low anion gap be a sign of a serious condition?
Yes, a low anion gap can sometimes reflect hypoalbuminemia, multiple myeloma, or lab error. While it is not always dangerous, it deserves review because it may point to a serious underlying problem.